PET-CT with FDG — radiological study
PET-CT of 11 Apr 2023 — images from the study
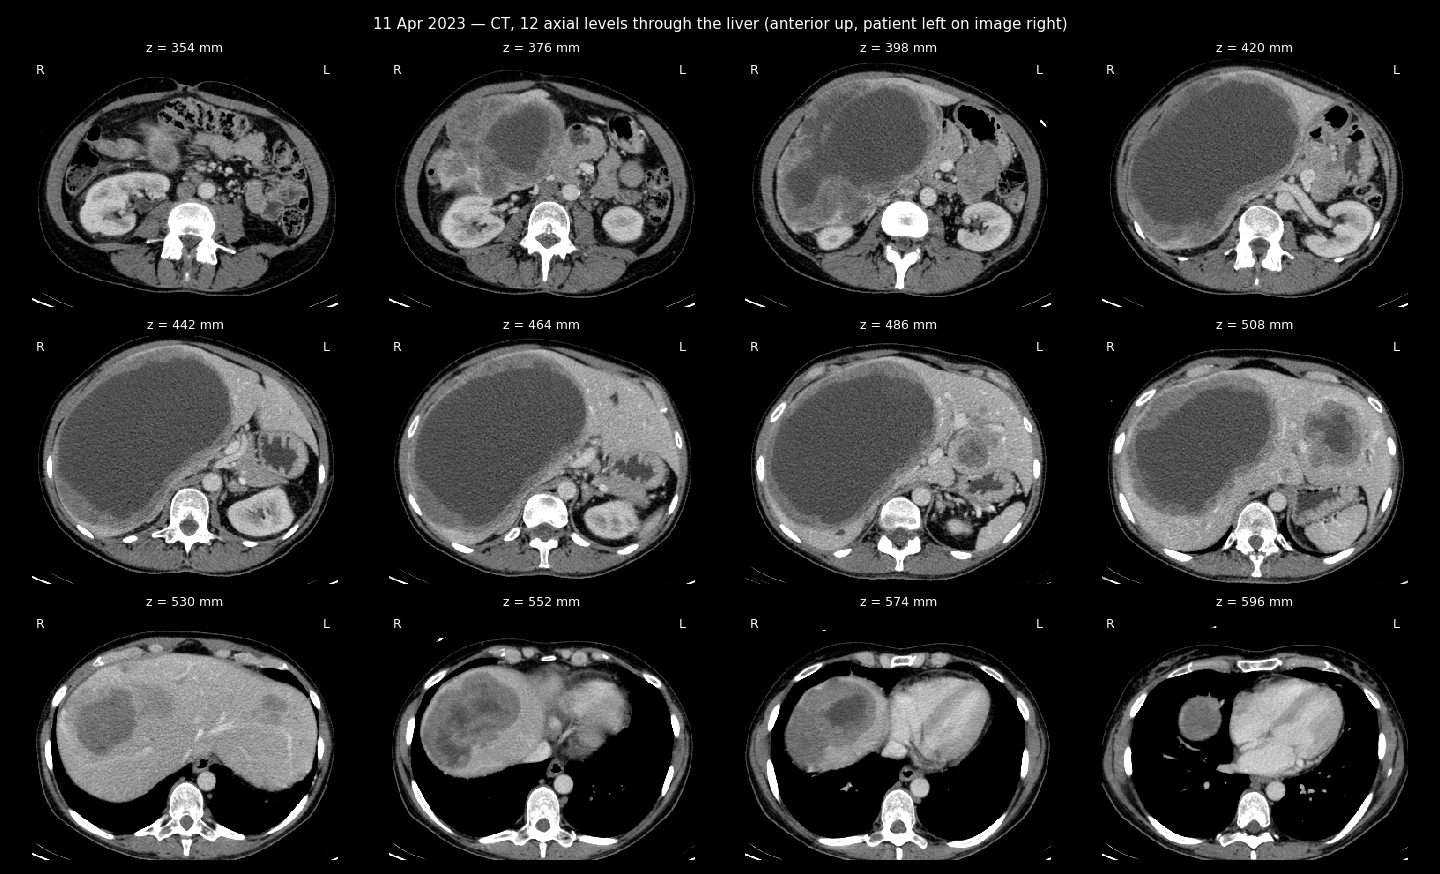
CT sheet, 12 levels through the liver
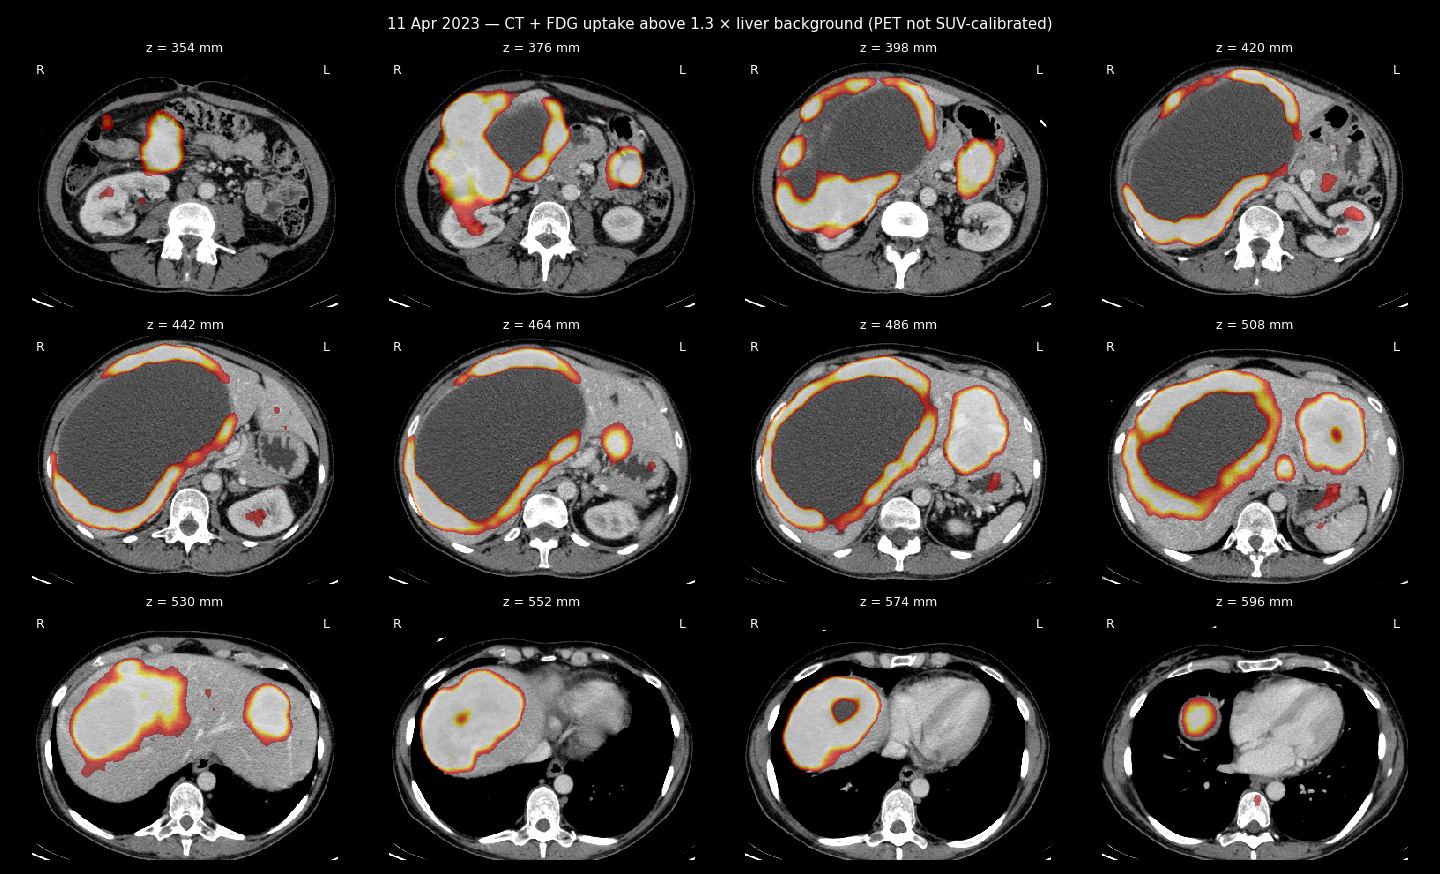
CT + FDG uptake sheet
LISOD
Israel Oncology Hospital
08720, Kyiv region, Obukhiv district,
village Plyut, str. Malyshka, 27
phone +38044 520 94 00
fax +38044 520 94 01
www.lisod.ua
Department of radiation diagnostics
Positron emission tomography combined with computed tomography with 18F-FDG
Patient: Zherlitsyna Anastasia Stanislavivna
ID 110889
Date of birth: 04-25-1976
Date of study: 11-04-2023
Methodology of the research
A PET/CT scan was performed from the level of the orbits to the middle of the thighs 65 waves after the intravenous injection of 10.5 mCi of 18F-FDG. The level of glycemia before the introduction of radiopharmaceutical preparation - 5.7 mmol/l.
CT scan was performed with intravenous contrast. An additional scan was performed at the level of the chest with a breath hold. Total DLP 1383 mGy*cm.
The attenuation correction of PET images was carried out on the basis of CT data. Standardized indicators of radiopharmaceutical preparation accumulation are normalized by patient weight (SUV).
Purpose of study/clinical data
Control radiological evaluation after the treatment
Data from previous studies for comparison/correlation CT 09-02-2023
Findings
Head and neck
Hypermetabolic changes typical for a metabolically active aggressive neoplastic lesion were not found; noticeable moderate asymmetry of the distribution of FDG in the area of the palatine tonsils, more to the left, without a separate mass or accompanying suspicious lymphadenopathy, non-specific, possibly inflammatory distribution.
Chest
Hypermetabolic changes typical for a metabolically active aggressive neoplastic lesion were not found; without significant structural dynamics, in particular, small pulmonary nodules.
Stomach and pelvis
Pre-visualized multiple masses in the liver with cystic/necrotic central components and peripheral, mostly hypovascular solid parts demonstrate high activity of solid parts, up to SUVmax/peak 11.1/9.8, relatively the most active components in the mass of the left lobe.
Compared to CT 02-2023 - a slight increase in the total size of the masses, for example, in the left lobe from 63 to 75 mm, the subdiaphragm in the right lobe from 90 to 101 mm, the dominant mass in the right lobe from 18 to 19 cm, also, the "thickness" of the peripheral solid components seem to be larger; no new similar nodules were found in the liver. Moderate expansion of the bile ducts distally/around the masses, more noticeable in the left lobe, without dynamics. Large vessels of the liver without visible blood clots.
Pre-visualized left mass centered between stomach and bowel loops/pancreas tail, and more gastric wall/submucosa in configuration, showing activity to SUVmax 8.2, slightly increased from 02-2023, from 55 to 58 mm max size.
Separate hypermetabolic lymphadenopathy was not found, retroperitoneal nodes up to 8-9 mm SAD with low activity.
Previously visualized masses/nodules in the uterus and in the right ovary with low activity (up to SUVmax 2.1), without significant changes in size from previous imaging, with no detectable new or hypermetabolic components.
Otherwise, without significant dynamics, no other active/suspicious lesions were found.
Bones and soft tissues
No hypermetabolic bone lesions were found, no structural/CT aggressive bone lesions were found
Radiological conclusion
The known masses in the liver and the mass on the left, which according to the configuration rather originates from the stomach wall, are metabolically active, with an insignificant increase in their sizes from 02-2023. Masses in the uterus and near/in the right ovary with low activity/no significant accumulation of FDG, structurally stable. No new individual suspicious/active lesions found since 02-2023. There are no previous metabolic data to assess metabolic dynamics. A significant difference in the activity of the liver/stomach and uterine masses allows us to assume different neoplastic lesions (in particular, primary aggressive from the stomach/GIST), or at least a significant heterogeneity in the activity/aggressiveness of the widespread lesion.
Faithfully yours, Novikov M.Y.
doctor radiologist,
head of the radiation diagnostics department
of the Israeli Oncology Hospital LISOD
